
Book 00 · Page 4141 / 80
Rhythms that kill, rhythms that wait
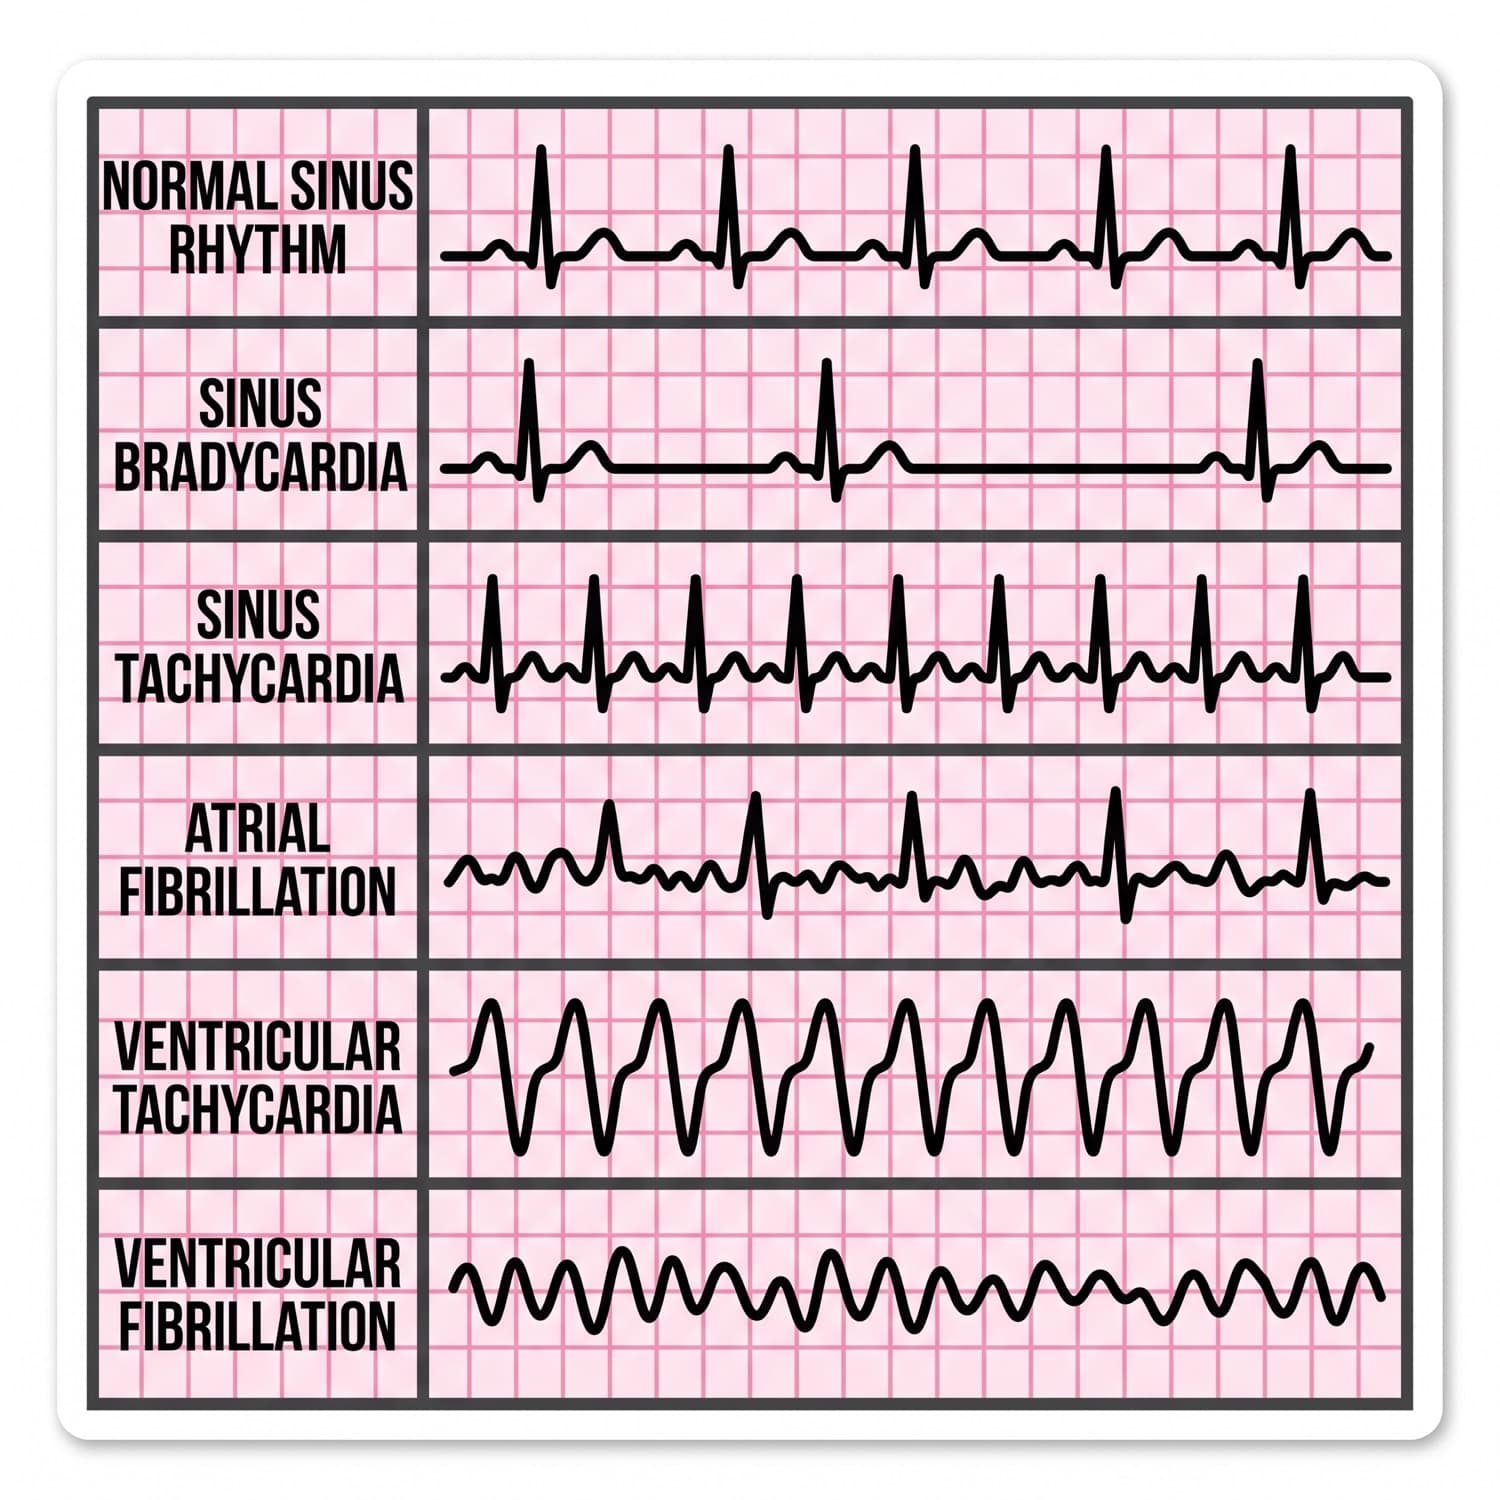
The exam rarely asks the candidate to measure a PR interval. It asks what to do next, and that answer comes from the patient, not the tracing. Sort every rhythm into the pile that changes the next sixty seconds.
| ACT NOW | ASSESS AND MONITOR | |
|---|---|---|
| Rhythm | Ventricular fibrillation, pulseless ventricular tachycardia | Sinus tachycardia |
| Asystole, pulseless electrical activity | Atrial fibrillation with a controlled ventricular response | |
| Torsades de pointes | First-degree block, Mobitz type I | |
| Complete heart block with hypotension | Infrequent asymptomatic premature ventricular contractions | |
| Pulse? | Absent, or present and unstable | Present |
| Stable? | No | Yes |
| First action | Compressions, then defibrillate the shockable ones; pace the symptomatic block | Find and treat the cause; continue monitoring |
| What they test | Can the candidate act without a diagnosis | Can the candidate resist over-treating |
Reading the left column
- Ventricular fibrillation and pulseless ventricular tachycardia have no perfusing pulse. Start compressions, defibrillate as soon as the device is ready, and resume compressions immediately afterward.
- Asystole and pulseless electrical activity are not shockable. High-quality compressions continue while the reversible cause is hunted.
- Torsades de pointes is a polymorphic ventricular tachycardia with a twisting axis. Magnesium is the treatment in the patient with a pulse; a pulseless patient gets defibrillation.
- Complete heart block with hypotension needs transcutaneous pacing, not observation.
Reading the right column
- Sinus tachycardia is a symptom. Find the fever, the pain, the hypovolemia, the hypoxia, or the anxiety driving it.
- Controlled atrial fibrillation needs a rate plan and a stroke-prevention plan, both of which are decisions, not emergencies.
- Mobitz type I lengthens the PR interval progressively and then drops a beat. Review contributing factors and keep watching.
The fork: No pulse sends you to compressions and the shock decision. Pulse present but unstable sends you to synchronized cardioversion. Pulse present and stable sends you to assessment.
Margin notetreat the patient; the monitor has no pulse.
Watch outnever delay compressions to interpret a rhythm.
TakeawayPulse first, stability second, rhythm name third.
→ BOOK 08 · P5 for strip interpretation · → BOOK 05 · P8 for the agents · → P40